The best contraceptive method depends on more than pregnancy-prevention power: your medical history, bleeding preferences, STI risk, privacy needs, and willingness to manage a schedule all matter. By the end, you will be able to compare methods, identify safety issues that require clinical review, and know what to do when protection is missed or fails.
Key takeaways
- Choose an implant or IUD when you want highly effective, low-effort pregnancy prevention.
- Use condoms for STI protection, including alongside another contraceptive method.
- Check migraines, blood pressure, breastfeeding, medications, and medical conditions before choosing hormones.
- Create a backup plan for missed pills, broken condoms, or suspected contraceptive failure.
Match the method to your pregnancy, bleeding, and privacy goals
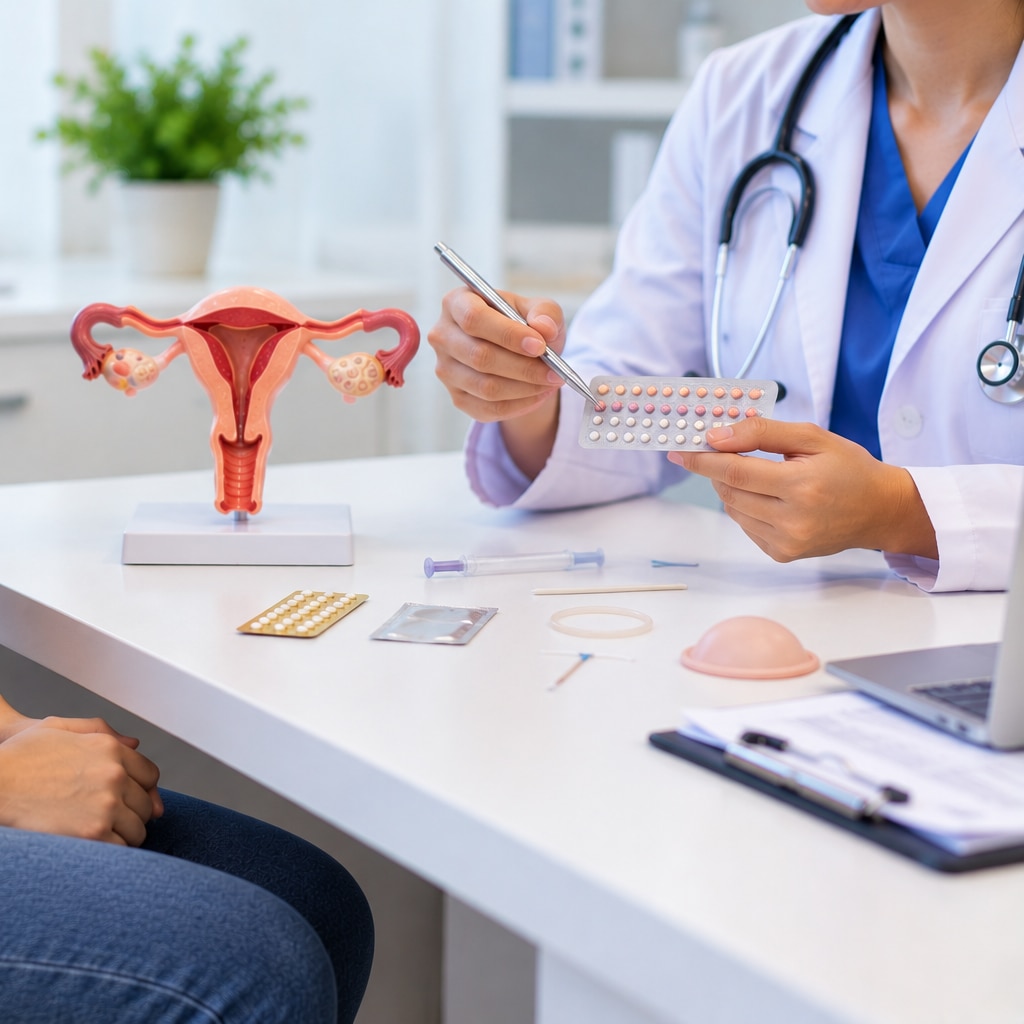
A 0.1% typical-use failure rate makes an implant or levonorgestrel IUD a stronger low-effort choice than a method you must remember daily. Your priorities—pregnancy spacing, hormone avoidance, bleeding control, privacy, or STI protection—should decide the trade-off.
| Option | User effort and duration | Hormones, bleeding, and privacy |
|---|---|---|
| Condoms | On demand; use every time | Hormone-free; reduce STI and HIV transmission risk when used correctly and consistently; external condoms have about 13% typical-use failure. Pair with another method when STI protection matters. |
| Combined oral contraceptive pills, patch, ring | Daily, weekly, or monthly; about 7% typical-use failure | Estrogen and progestin; may regulate bleeding; discreet, but supplies can be noticed. |
| Progestin-only pills | Daily, with careful timing | No estrogen; missed or late doses reduce protection; private if stored securely. |
| Injection | Repeat appointments; about 4% typical-use failure | Progestin; bleeding changes are possible; late appointments reduce protection. |
| Implant | One placement; about 0.1% failure | Progestin; unpredictable spotting can occur; highly private. |
| Levonorgestrel IUD | One placement; about 0.1–0.4% failure | Hormonal; periods commonly become lighter or absent; private. |
| Copper IUD | One placement; about 0.8% failure | Hormone-free; cramps and bleeding can increase, especially initially. |
| Diaphragm | Use during sex with spermicide | Hormone-free; correct placement is essential. |
| Permanent contraception | Vasectomy or tubal surgery | Treat as irreversible; choose only when ending childbearing is certain. |
An IUD or implant can suit adolescents and people who have never been pregnant. Choose condoms for STI protection, an IUD or implant for minimal effort, and a copper IUD when avoiding hormones matters most.
Check medical conditions before choosing estrogen, progestin, or no hormones
Migraine with aura contraception requires special caution: avoid combined pills, the patch, and the vaginal ring unless a qualified clinician identifies a safe alternative, because estrogen raises ischemic-stroke risk. This is central to estrogen contraception safety, not a decision based only on current symptoms.
| Option | Main health issue to check | Practical implication |
|---|---|---|
| Estrogen-containing methods | Aura migraine, clots, thrombophilia, stroke, cardiovascular disease, uncontrolled hypertension, liver disease, diabetes complications, or breast cancer | Often inappropriate; obtain individual medical review |
| Progestin-only pills, implant, injection, or hormonal IUD | Breast cancer history, liver disease, postpartum timing, breastfeeding, and other conditions | No estrogen restriction, but suitability still depends on your full history |
| Copper IUD | Heavy periods, severe cramps, and pelvic conditions | Hormone-free and unaffected by drug interactions, but can increase bleeding and cramping |
For smoking over 35 contraception decisions, combined methods become less suitable. Smoking 15 or more cigarettes daily is an unacceptable health risk; fewer than 15 daily means risks usually outweigh benefits. Progestin-only and nonhormonal methods are not restricted on smoking alone.
Breastfeeding contraception also depends on timing after delivery. Avoid combined hormonal contraception during the first 21 days; restrictions can continue through 42 days when other clot risks exist. Tell the clinician about blood pressure, liver disease, breast cancer history, diabetes complications, clot history, and every medicine or supplement before choosing.
Plan the start date, backup condoms, and medication checks
Protection can begin on insertion, on the day you start, or after a backup interval. The answer depends on the method and where you are in your menstrual cycle, so ask for the exact date when contraception starts working and when backup condoms can stop.
Use condoms throughout that interval and whenever STI or HIV protection matters.
| Method | Start and backup pattern |
|---|---|
| Copper or hormonal IUD | Protection starts immediately after insertion. |
| Implant, injection, combined pill, patch, or ring | Starting within the first 5 days of menstrual bleeding is usually immediate; starting later commonly requires condoms for 7 days. |
| Progestin-only pill | Backup depends on the product: some require 2 days, while drospirenone pills require 7 days. |
Do not assume every antibiotic causes contraception drug interactions. Ask a pharmacist or clinician to review every prescription, over-the-counter medicine, and supplement, including rifampicin, rifabutin, enzyme-inducing anti-seizure medicines, some HIV medicines, and St. John’s wort. Rifampicin contraception interactions are method-specific; do not stop prescribed treatment or trust a general internet list.
A copper IUD is unaffected.
Tell the clinician if vomiting or severe diarrhoea followed a pill; absorption may have failed, so use the product’s missed-pill instructions. Record injection dates because a late repeat injection reduces protection. Fertility returns quickly after most reversible methods, but after depot medroxyprogesterone acetate, ovulation commonly returns within about 15–49 weeks after the last injection.
Respond quickly to missed doses, broken condoms, and suspected failure
Act promptly after a missed contraceptive pill, a late contraceptive injection, vomiting, severe diarrhoea, or sex without reliable protection. Follow the exact missed-dose instructions for your product, use condoms until protection is restored, and ask about emergency contraception if unprotected intercourse occurred.
| Option | Timing | Key point |
|---|---|---|
| Copper IUD | Within 5 days | Ongoing contraception; unaffected by medication interactions |
| Ulipristal acetate | As soon as possible, within 5 days | Generally more effective than levonorgestrel later in the 5-day window |
| Levonorgestrel emergency contraception | As soon as possible, within 5 days | Effectiveness depends on timing and clinical suitability |
- If a broken condom breaks or slips, seek emergency contraception promptly. A copper IUD requires insertion by a trained clinician and provides continuing contraception.
- If vomiting or severe diarrhoea followed an oral dose, the medicine may not have been absorbed. Ask a pharmacist or clinician for product-specific instructions.
- After a late contraceptive injection, arrange the next dose promptly and use condoms until a clinician confirms when protection resumes.
- Tell the clinician about breastfeeding, body weight, timing, and medicines such as rifampin, rifabutin, enzyme-inducing anti-seizure medicines, HIV medicines, or St. John’s wort. Do not assume every antibiotic interferes.
- Emergency contraception does not end an established pregnancy. After ulipristal, ask when to restart hormonal contraception and how long to use condoms because starting hormones too soon can reduce its effect.
- Take a pregnancy test if your period is late or symptoms develop. Seek urgent care for severe one-sided pain, fainting, or heavy bleeding.
Turn your priorities into a method and follow-up plan
Write one priority first: temporary pregnancy prevention, spacing pregnancies, avoiding hormones, lighter or less painful periods, privacy, or the lowest possible user effort. Then record your deal-breakers before choosing.
- Migraine with aura, smoking at age 35 or older, high blood pressure, clot or stroke history, breast cancer, liver disease, diabetes complications, or breastfeeding
- Heavy periods or severe cramps
- Medicines or supplements that affect hormones
A clinician can use this list for a personalized contraception choice during contraception counselling.
| Option | Best fit | Main caution |
|---|---|---|
| Copper IUD | No hormones; lowest user effort | May worsen heavy bleeding and cramps |
| Hormonal IUD | Low effort; lighter periods | Insertion and initial spotting |
| Implant | Very low effort; spacing pregnancies | Irregular spotting is common |
| Injection, pills, patch, or ring | No device; reversible | Timely doses and medical screening |
| Condoms or diaphragm | On-demand, private, hormone-free | User technique; condoms reduce STI and HIV transmission |
| Permanent contraception | Certain you want no future pregnancies | Treat as irreversible |
Discuss bleeding before insertion or prescription. Implant spotting does not mean it has stopped working; new heavy bleeding needs evaluation for pregnancy, infection, medication effects, or another cause. Fertility return after contraception is usually rapid, but injection-related return can take longer.
If choosing vasectomy, use another method until semen testing confirms absent or sufficiently low sperm. In Thane, Dr. Jagruti Kadam 8048033934 can review postpartum status, bleeding goals, health history, and medication interactions before starting or changing contraception.
Related service
Family Planning Services ₹1000 Dr. Jagruti Kadam provides comprehensive family planning services designed to help individuals and couples make informed reproductive choices. View service → |
Frequently asked questions
How do I match contraception to my pregnancy, bleeding, and privacy goals?
Compare methods by effectiveness, desired pregnancy timing, bleeding changes, hormone preferences, ease of use, privacy, and STI protection. An implant or IUD suits low-effort pregnancy prevention, while condoms remain important for STI protection.
Which medical conditions should I discuss before choosing hormonal contraception?
Tell a clinician about migraines with aura, high blood pressure, smoking, blood-clot history, liver disease, breastfeeding, recent childbirth, and all medicines. These details help determine whether estrogen, progestin, or a non-hormonal method is appropriate.
When should I start contraception, and do I need backup condoms?
Ask when protection begins for the method you choose. Use condoms during the recommended backup period and check medicines for interactions before starting pills, implants, or other hormonal methods.
What should I do after a missed dose, broken condom, or suspected contraceptive failure?
Act promptly: follow the missed-dose instructions for your method, consider emergency contraception after unprotected sex, and arrange pregnancy testing when advised. Seek medical care for severe pain, heavy bleeding, or other urgent symptoms.